Optimal Fetal Position Makes Labour Shorter and Easier!

Fetal position (position of the baby in the maternal pelvis) at the onset of labour is one of the greatest determining factors of how the birth process will proceed.ย  The optimal fetal position is pictured below.ย  A good way to remember the best position is that if you can give your baby a back rub every time through your belly, then they are likely in a good position.

There’s lots you can do to affect the baby’s position. Read on!

The terms โ€œposteriorโ€ or โ€œsunny-side upโ€ describe a baby who faces out, or is spine-to-spine with the pregnant woman. โ€œOPโ€ is the medical jargon, meaning occiput posterior. The part of the head that enters the pelvis is bigger in this position and the baby doesnโ€™t flex and rotate as well as if they’re in the optimal position.ย  That can make for a much longer, more painful and more complicated birth.

Problems Related to Posterior Position

  • More difficult for baby to drop into and through the pelvis
  • Pregnancy may last longer
  • Membranes are more likely to rupture before the onset of labour
  • Labour may progress slowly or not at all
  • Back-labour – back-pain during labour that doesnโ€™t disappear between contractions
  • Increased risk of tearing
  • Increased risk of instrumental (vacuum or forceps) or Caesarean birth
  • Increased stress on babyโ€™s head and nervous system

Some women birth a posterior baby just fine.  Those include but are not limited to, women whoโ€™ve given birth without difficulty before, those with an average or smaller baby, a labouring woman whoโ€™s able to move about freely and allow her baby to rotate into an “anterior” (the optimal) position.

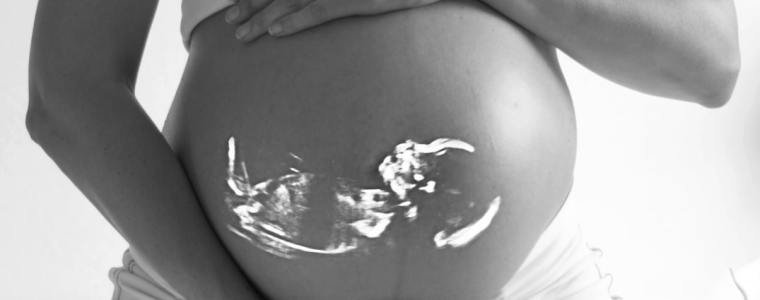
Fetus in WombBaby in optimal position:  head down and flexed, back out.

Signs of a Posterior Baby

  • Feeling kicks or flutters at the front
  • Frequent urination (more frequent than with anterior pregnancy)
  • Belly appears flat on top or lumpy
  • Your midwife or doctor can tell by palpating your abdomen or by doing an ultrasound
  • Fetal heart-tones may be difficult to hear
  • Head is not engaged or doesnโ€™t drop into pelvis
  • Can be assessed during labour by a cervical check

Factors Contributing to Posterior Position
Babies can assume a posterior position with no risk factors, but the following increase the chances:

  • North American lifestyle โ€“ reclining in upholstered furniture, sedentary lifestyle, sitting in cars (itโ€™s interesting to note this position is rare in cultures where pregnant women walk a lot or work bent-over, and lack Lazy-Boy style chairs and couches)
  • Sitting with legs crossed
  • Postural or anatomical issues
  • Issue of uterine / abdominal muscles (e.g. tight psoas)
  • First pregnancy
  • Epidural use early in labour (hinders rotation and descent of baby) is correlated with more than 3x the rate of posterior position at birth (Tully, 2008)
  • Labouring in bed or without adequate movement
  • Baby who was breech and turned to vertex (head down)
  • Pregnant person with history of breech or posterior baby
  • Short or tight cord around baby
  • Emotional issues – fear of birth or parenting, not paying attention to pregnancy, family history of breech, relationship issues, financial concerns, stress (Frye, 1998)

Tricks for Turning a Posterior Baby to an Anterior Position
Sometimes thereโ€™s an unknown reason for the baby to be posterior and nothing will turn them. But in many cases a baby can be turned. Please ask for details or referrals.

  • Visualization and โ€œtalkingโ€ to your baby. Focus on letting the baby know itโ€™s easier to get out when facing the other way.ย  This works especially well if combined with changing your emotional environment e.g. dealing with fears, prepping for birth.
  • Look at a picture of baby in proper position (e.g. Fig. 1), or have it drawn on your belly!
  • Webster Technique with a chiropractor certified in its use. Pistolese (2002) cites an 82% rate of success in relieving the musculoskeletal causes of intrauterine constraint. ย Itโ€™s beneficial to perform the Webster Technique starting at 35-36 weeks.
  • Sit with pelvis tilted forward – knees below pelvis with straight back. Instead of upholstered furniture, use a birth ball, the floor, a kneeling chair or a regular hard chair or stool
  • Hands and knees โ€“ read, crawl around, or do “childโ€™s pose” modified for pregnant belly
  • Pelvic rocking while on all 4โ€™s โ€“ gentle “cats and dogs” yoga postures โ€“ several times daily
  • Swimming or floating โ€“ anything with belly down like a hammock for baby to drop into
  • Movement and exercise
  • Sleep on left side with a body pillow โ€“ left leg straight, right leg bent on pillow
  • Homeopathic Pulsatilla 200CH, 1 dose every 3 days.
  • Acupuncture or moxibustion โ€“ see a Traditional Doctor of Chinese Medicine or an acupuncturist who specializes in womenโ€™s and pregnancy care.
  • Deal with fears around childbirth and parenting
  • Postural management – check out spinningbabies.com for some excellent postures and exercises that encourage babies to assume optimal positions for birth.
  • Exercises to prepare for birth and encourage pelvic floor health, and optimal fetal positioning, such as theย Miles Circuit.

Birth Trauma – Practical Tips for Preventing Trauma and Giving Birth After Trauma

There is a relationship between birth and trauma. Some people are traumatized through their birth experience while others begin the birth process in a traumatized state. Past trauma can have a significant impact in the birth room, including presenting additional challenges and the possibility of being retraumatized. This article presents practical tips for being more empowered and minimizing trauma during pregnancy and birth. 

Before we go further, I would like to acknowledge there are many obstetrical care workers who treat their patients respectfully and kindly while doing the important work of providing medical care. They are aware of the vulnerability of birthing families and treat them in a way that leaves them feeling safe, happy and whole. However, that is not the case everywhere or with everyone; thereโ€™s still work to do.

For most people birth in and of itself is not traumatic. In most cases, trauma stems from how they were treated through their birth. There are too many birth stories that include coercion, disrespect, disempowerment, fears that aren’t addressed, being left alone, feeling unsafe and unsupported, and lack of choices. Birthing people don’t know what their options are and therefore they have none. They don’t know how to prepare and what to do. They are told what’s going to be done to them rather than being part of the decision making process. Many women report feeling like they were stuck on a runaway train.

Women need to feel safe while giving birth. In fact, birth is shorter, more comfortable, and usually uncomplicated when thatโ€™s the case. There are things we can do to decrease or negate the impact of some common practices in the North American medical model of birth that may lead to feelings of vulnerability or trauma. In many cases itโ€™s just how things are done and set-up.ย 

Globally, 1 in 3 women have been subjected to physical and/or sexual violence. Every birthing person should be treated as a survivor but that is not the case yet. Fortunately in some hospitals, including ours, staff have special training in this area and provide extra respectful, sensitive and compassionate care to survivors.

Practises that may add to trauma in some people include…

  • Being exposed, naked, uncovered in front of others.
  • People who are fully clothed (and highly educated or seemingly โ€œin chargeโ€) standing over someone who is partially or wholly undressed, usually on their back, and possibly with their legs open, in a vulnerable state.
  • Being touched, especially from behind, without consent or even being told first. 
  • Language such as โ€œgood girlโ€ and โ€œhoneyโ€ and โ€œdearโ€.
  • Cervical checks in general. Exasperated by being told, โ€œIโ€™m going to check your cervix now,โ€ without a conversion to explain reasons, options, and waiting for consent. Painful cervical checks. Staff not stopping when being told โ€œNo!โ€ or โ€œStop!โ€ or any of the many other ways women say no or stop. 
  • Being put into positions, often presented as, โ€œYou have toโ€ฆโ€. Lack of choice.
  • Not being โ€œallowedโ€ to move freely.
  • Legs being held or put into leg rests / stirrups
  • โ€œPut on this gown.โ€ Being told what to wear, especially when that garment does not offer full coverage and is open in the back.
  • A room set up that results in โ€œprivate partsโ€ facing the door.
  • Technical language used in medical settings can be confusing and scary for some people.
  • Epidurals and the numbness that may result.
  • Not having timely access to pain medications, including epidurals.
  • Language related to failure or โ€œnot doing it rightโ€, e.g. lack of progress, making too much noise, breathing wrong, being too stiff, reacting too much to pain, stop crying.
  • Lack of choice in birthplace and/or medical care provider.

Things you can consider doing to feel more in control, more empowered, and lessen the chances of being traumatized:

  • Expect excellent and compassionate care but be prepared in case not everyone you meet feels that way to you.
  • Remember you have the same rights in the birth room as you do in the coffee shop or anywhere else! No one is allowed to touch you or do anything without your consent. You have the right to say โ€œyesโ€, โ€œnoโ€, โ€œwaitโ€, โ€œstopโ€ to any test and intervention. 
  • Be an active participant in your care. Consider your care providers as part of your team. 
  • Ask enough questions to make informed choices.
  • Pause. Normally things donโ€™t have to happen right away. Ask your questions, gather your wits, get grounded and then proceed.  
  • Bring a companion who can help you find your voice and help advocate for you. Doulas play an important role in this. 
  • Ask for a few minutes alone or with your support person(s) before making decisions. You might regroup, realize you have more questions, find the strength or means to say no to something you donโ€™t want, or yes to something you donโ€™t want but feels like the best choice. 
  • Maintain control over cervical checks and other procedures that might feel invasive. Donโ€™t proceed until the care provider has an understanding of how to help you feel as safe as possible.  
  • Share that you are coming into this experience with past trauma. No need to share details.
  • Hire a doula who is trauma-informed.
  • Say no. Use the word consent.
  • Wear clothing that feels safe and offers the level of modesty you need.
  • If you want touch comfort measures and also modesty, massage and touch can be done over a sheet or your clothing.
  • Consider how you might react to the intense sensations of birthing – pressure as the baby descends, pain and/or power of contractions, your body stretching. 
  • Tools to deal with the aforementioned sensations – meditation, hypnobirthing, comfort measures, pain medications including epidurals. Some people opt for cesarean. Discuss these options with your midwife/doctor if you are concerned. Your mental and emotional health are just as important as your obstetrical health.
  • Think about how it might feel to have an epidural that might cause legs to feel heavy or numbed. This can be a welcome relief or it might be frightening.
  • If you have a counselor or psychiatrist, have a meeting to help you prepare for birth and postpartum.
  • If itโ€™s not possible to be covered or positioned in a way that offers privacy from the door, then a companion can hold up a sheet or stand between you and the door, acting like a visual block as people enter & exit the room.
  • Wear headphones.
  • Wear a sheet or blanket like a fort or super-hero cape.
  • All the other things that bring comfort and security during birth.
  • Stick a sign on the door if thereโ€™s a single point you wish everyone to know. It might be, โ€œPlease read my birth plan before meeting me.โ€
  • Consider warm compresses on the perineum during crowning if youโ€™re on your back. This can offer warm comfort and a greater sense of privacy. On the other hand, some people would find this scary and like too much touch. 
  • Assume birthing positions other than being on your back, such as being upright, leaning forward, and hands & knees.  
  • If you normally wear glasses, consider the impact of leaving them on or off through labour. Seeing more or less detail may be helpful.

Things You Can Put on Your Birth Plan

You can create a nice Birth Preferences Document that builds bridges of communication and understanding with your medical care team. If you are a survivor or are vulnerable, then you may wish to include additional points related to trauma, which are listed below. It can be helpful to the staff if your document includes, โ€œDue to past trauma, โ€ฆ..โ€.  You don’t have to disclose and won’t be asked to explain what that trauma was. 

  • Wait for verbal consent before touching me in any way.
  • I need to have complete control over cervical checks, including when theyโ€™re done, by whom, and the pace. I may say โ€œyesโ€, โ€œnoโ€, โ€œwaitโ€, and โ€œstopโ€
  • Please assume I have not consented to anything until I expressly say yes. 
  • Before we discuss options, procedures and next steps, ensure Iโ€ฆ (options include: am fully clothed or covered, am sitting, am standing, have my partner/companion/doula nearby. Use any or all of those things in any combination). 
  • If Iโ€™m on the bed I will face the foot of the bed until the moment of birth. 
  • I will need a few minutes (alone?) to process information before making choices.
  • Please limit the team to essential staff only. No observers or students practicing on me.
  • Minimal cervical checks and only by experienced staff who will proceed only after obtaining my expressed verbal consent. 
  • Please use my name when addressing me; no terms of endearment such as honey or good-girl.
  • Please ensure I am covered as much as possible throughout my birth.
  • I would like warm compresses during crowning.
  • Hands off my bottom during crowning.
  • I would like to hear the baby heart monitor if it is being used.
  • Please silence the baby heart monitor if it is being used.

Preparing for your birth can include…

  • Getting as prepared as possible before giving birth. Learn about local practises and your options. Knowledge is power! My prenatal classes are designed with this in mind.
  • Work with a midwife or doctor with whom you feel safe and comfortable.
  • Hiring a doula. Most communities have a professional association with bios for a variety of doulas.
  • Practising saying no to things you don’t want and yes to those you want. Ask for what you want.
  • Taking steps to learn your options – prenatal classes, appointments with your medical care provider, counsellors, local birth-workers – and prepare a plan for your specific concerns.
  • Practising the things you might want to do in labour, such as a variety of positions, comfort measures, grounding practises, moving freely in clothing you wish to wear in birth.
  • A hospital tour. The fewer surprises the better.
  • Pack a birth bag that includes choices of clothing, things you can use for comfort, and even a couple of things that bring you peace.
  • Asking lots of questions along the way. Practise having discussions with your team in order to have shared decision making. When you say “no” that should be respected and when you say “yes” you’ll feel better about your decision. You will likely be pleasantly surprised.

Checklist and Tips for Making a Birth Plan

Most people who give birth in a hospital are meeting their medical care team for the first time. A good birth plan, which I prefer to call โ€œBirth Preferencesโ€, can build bridges with your medical team. It can help them get to know you and quickly understand what youโ€™d like in your ideal birth.

Before creating your Birth Preferences, learn about the policies and practises at your birthplace, so you know what to put on your wish-list. If you have special circumstances then you can incorporate those into your birth plan. Examples include choices in caesareans and considerations for trauma reduction.

Your Birth Plan document should be only one page with lots of white space and an easy font – at least 12pt. Use respectful and positive, but firm language. โ€œI preferโ€ฆ.โ€ is wishy-washy for something that really matters to you. 

I recommend you use language that reflects who you are. If you have a great sense of humour, feel free to insert fun and levity in your plan. โ€œIf Jamie takes a nap, please kick him when he starts snoring.โ€

Checklist for an excellent Birth Preferences document

This section includes examples. Feel free to copy them or use your own language. 

  1. Start with an opening paragraph that includes:
  • An opening statement that encompasses your attitudes or overall vision e.g. โ€œWeโ€™ve prepared for a natural birthโ€ or โ€œAn epidural is part of my planโ€ or โ€œWeโ€™re using Hypnobirthing as a tool.โ€
  • A statement about consent, such as โ€œWeโ€™re open to changes after discussion with the medical staff so we can make informed choices.โ€ or โ€œI will ask questions whenever a procedure is recommended and then need a few minutes alone to think.โ€
  • A kindness to the staff. โ€œThank you for supporting us through our birth processโ€ or โ€œWe appreciate the work you do.โ€
  1. An additional opening paragraph if there are special circumstances:
  • Medical conditions that need to be known urgently, such as โ€œLucy is allergic to penicillinโ€. 
  • Mobility issues or cognitive considerations.
  • Sensitive issues that may affect your birth, if it feels safe to share. (Itโ€™s been my experience that this level of personal sharing makes for better treatment.) โ€œDue to previous trauma, no one is to touch me until I am aware of who they are, understand why and whatโ€™s involved, and have verbally agreed.โ€  Or โ€œRobin faints at the sight of blood, even one drop.โ€ Or โ€œWeโ€™ve had a previous loss and do not want to discuss it. Please see the prenatal records.โ€
  1. Then a short list of points for your wishes. It could be titled, โ€œThese are our wishesโ€:
  • If anyone is joining you, name them. E.g. Your doula or โ€œplus-oneโ€ such as a friend or mother.
  • The environment youโ€™d like, such as quiet with dim lights, loud rocking music (bring your own), window blinds open for sunshine, privacy.
  • Continue this section with points that are unique to you. Here are a few of my favorite things from the hundreds of birth plans Iโ€™ve seen:
    • I must wear my purple socks at all times.
    • Do not offer pain medications; Iโ€™ll ask if I want anything.
    • Please run a bath and encourage me to get in.
    • Minimal cervical checks and only by experienced staff.
    • I will eat if Iโ€™m hungry; please provide a waiver.
    • Please provide the squatting bar and recommend positions to keep labour moving.
    • Please coach me through pushing. 
    • I will breathe my baby down and appreciate quiet during the bearing-down stage.
    • Essential staff only; no observers or learners. 
    • Students are welcome.

You get the idea!

  • Cord and placenta plans, if any. E.g. Weโ€™d like 3 minutes of delayed cord clamping. Or Weโ€™re keeping our placenta. Or Please show me the placenta before disposing of it.
  1. Some people add an โ€œIn case of Caesarean:โ€ heading, with things that are important to them such as playing a certain song, delayed cord clamping, requesting someone to take photos if possible, keeping family together as long as possible in the OR.
  1. A closing sentence such as โ€œThank you for taking time to read this pageโ€ or โ€œThank you for being part of our big day!โ€

Do not include:

  • Disaster planning language e.g. โ€œ… unless something goes wrong.โ€ or โ€œ… unless itโ€™s neededโ€.  Itโ€™s a given. 
  • Things that arenโ€™t issues. If your local hospital has a policy that all babies are held skin-to-skin by a parent immediately upon birth and for the first hour (thatโ€™s the policy in my local hospital), then thereโ€™s no need to ask for that. 
  • A shopping list of all the things you donโ€™t want. You donโ€™t have to tell your medical team that you donโ€™t want an episiotomy or a caesarean – they know that. (Well, unless youโ€™re in a place where episiotomies are routinely done – then add that to the list! In almost every Canadian hospital, episiotomies are not routinely done.)
  • The interventions that are only done after discussion, such as induction, which requires a conversation and signed consent form. 
  • Postpartum care of the maternal or newborn patient. โ€œI will breastfeedโ€ or โ€œI will use formulaโ€ do not belong on the birth plan. 

Need help to make a birth plan that builds bridges instead of walls?

I can help you sort through your options and find the best wording. Check out my Birth Plan Prep Consultations which are available in person or on Zoom.

Doula Interview Questions

Most doulas offer a complimentary initial meet-n-greet to determine if you’d be a good fit to work together. It’s an opportunity to learn how the doula works, their point of view, what they offer, and also to share what you’d like for your birth and support, if you know. Many people don’t know much about what kind of birth they want to plan; experienced doulas can help sort that out.ย  After all, if you don’t know your options, you have none.

People learn all about their options and choices (there are many!!) in my Prenatal Classes.

Here are some questions you might wish to ask when you’re considering working with a doula for your birth.

BACKGROUND, EDUCATION, PHILOSOPHY

  1. How many births have you attended?
  2. How long have you been in practise?
  3. Where have you worked? (Hospitals, birth centres, homes. Which ones?)
  4. With which primary practitioners have you worked in my area? (Midwives, doctors, OBs).
  5. Whatโ€™s your educational background in general?
  6. What experience, education and training do you have, specifically related to birth (childbirth education, birth support, breastfeeding, postpartum support and newborn care)?
  7. Do you have complimentary training e.g. natural remedies, modalities for pain management & comfort measures?
  8. What is your philosophy about pregnancy, birth and support?
  9. What’s one thing you wish all parents-to-be knew about birth?
  10. Are there limitations of support?ย  E.g., natural vs. medicated birth, time-lines for gestation & labour, home vs. hospital birth.
  11. What compelled you to start doing this work?

GENERAL PRACTISE ORGANIZATION

  1. What are you affiliations? e.g. Professional associations, memberships
  2. Do you provide community links and resources for and relationships with other practitioners with skills who may benefit pregnant and postpartum people?
  3. Whatโ€™s your offer, in detail? e.g. # of prenatal visits, on-call schedule, post-partum support/schedule.
  4. Fees – cost, payment schedule, return policy. What payments do you accept? Do you offer payment plans?
  5. How do you support partners / birth-companions?
  6. How do you like to communicate with your clients?
  7. What expectations do you have of your clients?
  8. Do you have privileges in all or limited birth centres & hospitals?
  9. Do you work with out-of-town clients?
  10. Are there additional perks? Are they included or do they cost extra? e.g. Lending library of books & videos, informational resources, health related therapies, workshops or classes?

PRENATAL CARE

  1. What information is covered in prenatal meetings?
  2. Do you help create a birth-plan?
  3. What kind of preparation tools/materials do you offer?
  4. How do you help prepare clients for their ideal birth?
  5. Do you expect your clients to do any homework?
  6. Do you help your clients prepare for the postpartum stage? If so, how?
  7. Are you available for extra meetings, questions, phone calls? If so, are there additional fees?

LABOR & BIRTH

  1. Do you work with back-up? If so, who and can I meet them if I wish?
  2. Under what circumstances would the back-up attend?
  3. What if you miss the birth?
  4. What if I go into labour before on-call dates?
  5. When do you join your clients in labour?
  6. Where do you join your clients? At home or place of birth?
  7. How long do you stay?
  8. What are your methods or tools for support during the birthing process? e.g. Pain management techniques such as massage & knowledge of positions; complimentary therapies such as homeopathy, acupuncture, aromatherapy.
  9. How do you help keep labour progressing efficiently?
  10. What do you do to help with difficult labours (long, stalled, and/or back labour)
  11. Are you knowledgeable and comfortable supporting labour with medical interventions?
  12. How do you work with my partner and/or anyone else I might wish to be part of my labour?
  13. What if I have a Caesarean birth?
  14. What if Iโ€™m transferred to (another) hospital or city?

POSTPARTUM & NEWBORN CARE

  1. Do you help with breastfeeding? How? When? e.g. Immediately after birth or at home in the following days too?
  2. What if I need specialized help with breastfeeding and/or recovery from birth?
  3. What does your support look like in the postpartum stage?
  4. How long do you offer postpartum support?
  5. Do you have resources to help with postpartum recovery? For the birthing person and/or the baby?

MOST IMPORTANT NOTE FOR PARENTS-TO-BE:

  1. Do you feel comfortable enough with this doula to share your babyโ€™s birth?
  2. Are they kind, warm, and have the other personality traits you’d like in a doula?
  3. Is the doula knowledgeable about your particular concerns?
  4. Do they listen and communicate well?
  5. Are they comfortable with your choices or do they seem to have their own agenda?

Angie The Doula – Guide on When To Go To The Hospital

If youโ€™re planning a hospital birth then you have to figure out when to go. This guide will help you make that important decision.

Most people donโ€™t know that the majority of naturally-starting labours is usually done at home. Some people want to get to the hospital later in the birth process. They know the longer theyโ€™re in the hospital, the more likely they are to have interventions as part of their birth. They may simply enjoy being at home for longer.ย 

One of the benefits of working with a doula is that we help clients decide when to go. We will remind you that you won’t be officially admitted if you aren’t โ€œfar enough alongโ€ in labour. Most first time birthers without professional guidance go far too early, often by many hours. This leads to the disappointment of being sent back home.ย 

Please note that this is a general guide. At your prenatal appointments, ask your medical care provider if there are any specific recommendations for when you should go in. Some pre-existing conditions or medical issues lead to different recommendations from those below.

Photo by Paula O. Licensed under Attribution 2.0 Generic (CC BY 2.0)

When to go to hospital

Unless youโ€™ve been told otherwise by HCP…

  • Pattern of contractions or sensations (explained below): 311 for a first birth or 411 for subsequent births; even sooner if you have a history of fast birthing. Hot tip: If you feel like eating, then itโ€™s likely too early, based on labour pattern alone.
  • Lots of pressure down low. If contractions end with a grunt or feelings of needing to poop, then get going!ย 
  • Any signs of labour before 37 weeks.
  • Any health concerns (some โ€œwarning signsโ€ are below).
  • Decreased fetal movement that isnโ€™t remedied within an hour or two by eating and resting. This is not a 911 call but it does mean to go presently. Do not sleep on this.
  • When waters release? Maybe, maybe not.
  • If thereโ€™s a colour (yellow, brown, green) or foul odour when waters release.
  • Want pharmaceutical help coping with pain.
  • Feel safer at the hospital or want reassurance about your own or babyโ€™s health. You will likely be sent home if all is well and you are not in โ€˜active labourโ€™ but that’s OK. Consider it a trial-run and some good news that everyone is medically stable.

Before heading in:

  • Have some juice or snack (unless youโ€™ve been instructed to not eat e.g. schedule c/s).
  • Pee before heading out the door.
  • Bring:
    • Health Card
    • Envelope with your prenatal records & birth-plan
    • Any prescription medications
    • Bonus: lip-balm and a hair-tie
  • Be ready to answer these 3 questions:

1.ย  ย  Whatโ€™s the labour pattern (just show an app if you’re using one)?

2.    Have waters released? If so was there a colour? 

3.    Is the baby moving normally?

Warning Signs

This is a partial list. Warning signs are covered in detail in prenatal classes and health region documents.

Seek medical attention (do not sleep on these signs or wait in hopes that they pass):

  • Decreased fetal movement
  • Visual disturbances
  • Sudden and severe headache
  • Pain in upper abdomen that doesnโ€™t pass
  • Maternal fever

911 call:

  • Red, flowing bleeding or clots
  • Sudden, severe / intense / sharp pain that brings you to your knees and doesnโ€™t pass
  • Cord prolapse when waters release

A note about โ€œbeing sent homeโ€: Itโ€™s OK. Perhaps itโ€™s inconvenient but it can be reassuring to get checked out, be found healthy, and then be sent home. Iโ€™ve met a lot of nice staff at various hospitals who will tell you itโ€™s better to come in for nothing than to miss a problem.  

Note about the contraction pattern: 

  • 311 means 3 minutes between the start of one contraction and the start of the next; 1 minute from start to end of the contraction; at least 1 hour of that pattern consistently. (411 is the same except 4 min between contractions.) 
  • Use 411 as your guide if you wish to get there soon into active labour, and likely stay but maybe sent home . 
  • Use 311 as your guide if you want to be more certain of being admitted and have no need or desire to go earlier in the process

I teach a variety of Child Birth Education classes and prenatal workshops online for people all over.  I have been a birth doula since 2002, and have helped over 300 clients with their births and over 1000 through prenatal classes. Learn more about my birth doula services, and contact me with any questions you may have.

Making Informed Choices

You know informed choice is a legal right but how do you make those choices? Here’s some guidance to help you get information and ask questions, so you can be an active participant in your health care.

While tests and interventions may not be introduced in a way that implies they’re optional, they are. Everything is optional. In my experience personally and as a birth attendant, medical staff are patient, respectful and happy to answer questions when asked.

Brewer Pregnancy Nutrition

Good quality nutrition, including adequate protein, is required for the increased metabolic functions that occur during pregnancy. Many midwives and practitioners recommend the Brewer Diet. Thereโ€™s an overwhelming amount of evidence to support this recommendation. Studies from Harvard find that eating 75 grams of protein daily helps prevent diseases of pregnancy such as pre-eclampsia (Abubakar, A., & al. (2011, Aug)).

In the 1960โ€™s Dr. Tom Brewer worked with a large, high-obstetrical-risk group in California: impoverished ethnic minority teen mothers in their first pregnancy.ย  During the same time in other areas of the USA, this group had up to 35% rates of serious pregnancy diseases, preeclampsia and eclampsia. Dr. Brewer worked with more than 7000 pregnant women over more than 12 years. He asked each woman about her diet and determined that malnutrition was prevalent.ย  All of his clients were required to attend nutritional counselling and were fed good nutrition and adequate protein.ย  The incidence of serious pregnancy illnessesย  among his patients dropped to 0.5% (Brewer & Brewer-Krebs, 1977)! This is remarkable and well documented but as there was no โ€œcontrol groupโ€ (a group who didnโ€™t receive โ€œtreatmentโ€, because Dr. Brewer felt it would be unethical to withhold good nutrition from a group of pregnant women), most medical associations donโ€™t consider this scientifically valid research.

The basic Brewer diet recommends a daily minimum of 2600 calories, 80-120 grams protein, salt-to-taste, green veggies, whole grains, fats, and vitamin-rich foodsย (Jones).ย  The Brewer diet can be easily integrated into general good pregnancy nutrition (see Basic Prenatal Nutrition handout (Evans, 2011)).ย  For example, while the Brewer Diet doesnโ€™t specify types of salt or fat, whole-mineral salts (e.g. Himalayan or Celtic) and high quality omega-3 fats are healthiest.ย  Special needs such as food-sensitivities / allergies, ethical choices or cultural habits can all be incorporated into the Brewer Diet.ย  As usual, ensure you eat 3 meals and 3 snacks daily, including protein at each one.

If you wish to check out the actual โ€œBrewer Dietโ€, see Dr. Brewer’s Pregnancy Diet Checklists, which include vegan and vegetarian options. Of course you can make substitutions based on your practices and preferences. If you don’t drink milk, sub it for another protein source with calcium. Below is a basic checklist you can use.

Brewer Pregnancy Diet Food Log

The list below is the minimum daily requirements according to Dr. Brewer.ย  You may wish to consult a holistic nutritionist if you have special needs or if you’re having trouble meeting these daily minimums as this requires prompt attention.

Check off a box each time you have a serving.ย  Each food counts as one checkmark on the lists e.g. a glass of milk counts as either “Milk” or “Protein”, but not both.ย  Examples for each category are presented.ย  Modify to fit any special considerations you have, such as vegetarian or a health issue to work around.

DAILY MINIMUMS:

โ–ก โ–ก โ–ก โ–ก โ–ก โ–ก โ–ก โ–ก (8) Calcium source; servings below.ย  Note 125ml = ยฝ cup

ยฝ cup animal milk, yogurt or sour cream

ยผ cup cottage cheese

1 small slice cheese

36 almonds

12 Brazil nuts

1 tbsp raw sesame seeds

1/3 cup cooked bok choy or collard greens

1 cup broccoli, cooked

ยฝย  cup kale

2 teaspoons blackstrap molasses

4 oz black olives

1 oz sardines

โ–ก โ–ก โ–ก โ–ก โ–ก โ–ก โ–ก โ–ก (8) Protein; servings below.ย  1oz = 7g.

Note:ย  See information about fish and mercury on Basic Prenatal Nutrition handout.

1 oz poultry, fish, red-meat, or organs

ยผ cup canned salmon or tuna

3 sardines

1 oz cheese: cheddar, Swiss, other hard cheese

ยผ cup cottage cheese

1/8 cup brewer’s yeast + 1/4 cup rice

1/8 cup sesame or sunflower seeds + ยฝ cup cup rice

1/8 cup beans + 1/4 cup whole rice or ยฝ cup cornmeal (measured before cooking)

โ–ก โ–ก (2) Fresh, dark green vegetables; servings below

1 cup broccoli

1 cup brussels sprouts

ยฝ cup lettuce (preferable romaine)

ยฝ cup endive

ยฝ cup asparagus

ยฝ cup sprouts: bean, alfalfa

2/3 cup greens e.g. collard, turnip, beet, mustard, dandelion, kale, spinach

โ–ก โ–ก โ–ก โ–ก โ–ก (5) Whole grains; servings below

1 slice whole grain bread

1 corn tortilla

ยฝ cup oatmeal, brown rice, quinoa,

1 shredded wheat biscuit

ยฝ cup bran flakes or granola

ยผ cup wheat germ

1 waffle or pancake made from whole grain

ยฝย  roll, muffin, or bagel made from whole grain

โ–ก โ–ก (2) Vitamin C foods; servings below

ยฝ grapefruit

ยฝ cup grapefruit juice

1 orange

ยฝ cup orange juice

1 large tomato

1 cup tomato juice

ยฝ cantaloupe

1 lemon or lime

ยฝ cup papaya

ยฝ cup strawberries

1 large green pepper

1 large potato, any style

โ–ก โ–ก โ–ก (3) Fats and oils; servings below

1 tbsp butter

ยผ avocado

1 tbsp nut-butter

1 tsp algae oil

1 tbsp first/cold-pressed vegan oil โ€“ olive, flax, avocado, hemp, coconut

1 tsp cold-pressed fish oil โ€“ cod-liver, sardine, mackerel, anchovy, krill

โ–ก (1) Vitamin A foods; servings below

3 apricots

ยฝ cantaloupe

ยฝ cup carrots (1 large)

ยฝ cup pumpkin

ยฝ cup winter squash

1 sweet potato

Salt and other sodium sourcesโ€”unlimited, to taste

kelp powder–to taste

soy sauce or tamari–to taste

full spectrum natural salt to taste โ€“ Himilayan, Celtic i.e. grey or pink salt

Waterโ€”unlimited; drink to avoid thirst, not in response to it

Purified water is best โ€“ see http://www.angieevans.ca/pdf/Water%20&%20Hydration.pdf

Fresh, home-made juice

Unsweetened herbal tea (see Safe Herbs in Pregnancy handout)

References

Abubakar, A., & al. (2011, Aug). Lipid Profiles and Platelets Counts of Pre-eclamptic women in Selected Rural Areas of Northern Nigeria. ย WebmedCentral PHYSIOLOGY: http://www.webmedcentral.com/article_view/2121

ACOG. (2002, Jan). Diagnosis and Management of Preeclampsia and Eclampsia; #33. ACOG Practise Bulletin – Clinical Management Guidelines for Obstetrician-Gynecologists: http://mail.ny.acog.org/website/SMIPodcast/DiagnosisMgt.pdf

Brewer, D. T., & Brewer-Krebs, G. (1977). What Every Pregnant Woman Should Know. The Dr. Brewer Pregnancy Diet: http://www.drbrewerpregnancydiet.com/id74.html

Evans, A. (2011). Basic Prenatal Nutrition. Canmore.

Frye, A. (2007). Understanding Diagnostic Tests in the Childbearing Year, 7th Ed. Portland, OR: Labrys Press.

good nutrition… for healthier moms and babies. (n.d.).ย  BlueRibbonBaby.org: http://www.blueribbonbaby.org/

Haas, A. (1995). Preventing Preeclamsia, PIH, Toxemai and HELLP by Good Nutrition. Midwifery Today .

Jones, J. M. (n.d.).ย  The Dr. Brewer Pregnancy Diet: http://www.drbrewerpregnancydiet.com/

Maine, D. (2000). Role of nutrition in the prevention of toxemia. The American Journal of Clinical Nutrition , 72 (1), 298-300.

NICE. (2010, Aug). NICE clinical guideline 107: Hypertension in pregnancy. NHS – National Institute for Health and Clinical Excellence: http://www.nice.org.uk/nicemedia/live/13098/50418/50418.pdf

Summer pregnancies & hot births!!

Oh, the days are hot and even more so when we’re growing a baby or holding a newborn. If you don’t already know, profuse sweating is a normal part of postpartum recovery even during winter.ย 

Here are some tips for summer survival with a baby-bump that go beyond the obvious, typical lists – wear loose clothing, do things early in the day, stay hydrated, find AC. I think we all know that by now.  

Summer Pregnancy-Safe Drinks

Growing and/or feeding a baby both take a lot of energy and we burn through more electrolytes and minerals in the hot summer. Sugar drinks are not helpful. Pregnant and breastfeeding bodies are more susceptible to blood sugar shifts and the yeast / thrush infections that result from high sugar intake. I have 2 articles for you for healthy, refreshing and cooling drinks (other than plain old water which is of course, important every day). They’re all nutritive during pregnancy and postpartum recovery – actually any time. Kids and adults can consume these.ย 

Cooling Essential Oil Body Sprays / Mists

Even though every bottle says “don’t use during pregnancy”, there are a lot of oils that are safe. Consult a certified aromatherapist – that’s me, from way before it was cool (pun intended) to be into essential oils. You can make a spritzer with:

  • mint
  • lavender
  • cucumber
  • lemon – actually any citrus oil.

Add any combination of those to aloe, witch-hazel or a flower water such as rosewater.

If you prefer to buy a spray, check out the perineum sprays such as that made by Earth Mama Organics. They can be used all over, not just your bottom! 

Caution #1:ย Citrus oils can make your skin more sensitive to sun-burn; only use for an indoor spray.
Caution #2:ย Many commercial refreshers and cooling sprays contain Eucalyptus, which should never be used near babies and pets. Best to avoid it through pregnancy too. Some types are safe but the most commonly used ones are too strong.ย 

Angie’s Tips for a Cooler Birth:

  • Put a small wireless fan in your birth bag and/or birth place. Some of my clients use handheld fans and others use ones with a big clip.ย 
  • If you’re having a hospital birth, i.e. in a scent-free environment, then bring an empty squirt bottle and fill it with cold water for misting.ย 
  • Ice chips! They’re amazing during labour & birth. Suck on them, put them in a washcloth and use as a cold-pack all over the body, put them in a bowl of water and dip a washcloth in to apply on foreheads and necks, add them to juice and water. I rarely attend a birth without using at least a couple of cups of ice-chips.ย 
  • Temperature fluctuations are amplified during the birth process. This video has tips to regulate temperature during birth and what the partner / birth companions can do.ย ย 

Essential Herbal Tea for Pregnancy & Breastfeeding

Women have consumed infusions (tea) of Red Raspberry leaf and Nettle leaf through the ages for a healthy childbearing year, healthy reproductive organs at any stage of life, and to keep their skin soft and supple.ย  This blend is high in easily absorbed minerals.ย  If no milk or sugar is added then this drink counts toward your daily water intake.

Drink 1-3 cups of Pregnancy Tea, hot or cold, daily through first 2 trimesters, and 3 cups during last trimester.ย 

Combine these teas in any ratio you wish, but the general recipe is:

  • 2 parts Red Raspberry Leaf
  • 2 parts Nettle Leaf
  • 1 part Horsetail Leaf (added for calcium & strong bones)
  • Optional: 1 bag or small scoop of lemon, berry/fruit teas (ensure no licorice), mint or lemongrass to change up the flavour.

A batch can be stored in the fridge for up to 3 days.

Red raspberry leaf (Rubus idaeus)

  • Most commonly used and well-known pregnancy herb
  • Tones female reproductive system; also pelvic and uterine muscles
  • High amounts vitamin C, easily assimilated calcium and iron
  • Also vitamins E, A, B-complex, many minerals inc phosphorus and potassium
  • High mineral content helps tissues stretch, decreases stretch marks, helps prevent anemia
  • Lower rates of miscarriage and postpartum hemorrhage
  • Prepares body for labor. Therefore decreases pain and length of labor.ย  Doesnโ€™t strengthen contractions but makes them more efficient.
  • Help expel placenta
  • Good for morning sickness
  • NOTE: Red raspberry leaf tea does not induce labour! Not sure where that rumor started but it’s not true. Don’t down buckets of this hoping to bring on labour.

Nettle (Urtica dioica)

  • High amounts of virtually all mineral & vitamins needed for health
  • Especially high in A,C,E,D,K, calcium, potassium, phosphorus, iron, sulfur
  • High amounts of chlorophyll (for energy and nutrients, vitamin K)
  • Nourish and strengthen kidneys; gently dislodge and dissolve any mineral buildup
  • Relax leg cramps and muscle spasms
  • Prevent hemorrhage after birth due to high vitamin K
  • Strengthens blood vessels, therefore good for hemorrhoid prevention
  • Astringent for hemorrhoids
  • Increases quality of breast milk

Other herbs high in easily-assimilated vitamins and minerals (alone or added to the above teas) include Horsetail a.k.a. Shavegrass (very high in calcium), Alfalfa and Kelp.

Several other herbs are safe during pregnancy and are tasty e.g. mint.ย  Some aid pregnancy related issues such as nausea, heartburn, cramping, and constipation to name a few.ย  These include but are not limited to ginger, chamomile, slippery elm bark, and fennel.ย  Consult a qualified herbalist with knowledge of pregnancy herbs before taking any.

By the way, this tea is healthy for the males in your life too, and is safe for all ages from infancy on.ย  Itโ€™s a lovely, mildly flavoured drink for the whole family.

Prefer pre-packaged tea?ย  Health stores and quality Mama/Baby stores sell pregnancy tea, e.g. Earth Mama Organics โ€œThird Trimester Teaโ€ (which you can take in any trimester).

C-19 Updates in Birth and Postpartum Care in Regina

I’ve been keeping in touch with the good people managing the units at Regina General Hospital. Here are all of the recent updates of RGH Labour/Birth Unit and Mother/Baby Units here in Regina, Saskatchewan due to Covid-19. Please note that any of these may change on short notice due to the coronavirus pandemic.

Some additional tips for navigating your birth journey:

I lead RGH Tours live but online multiple times a month.

Article:ย How to Set Up your Birth Room (i.e. What Your Doula Would Normally Do!)

Easing Labour Pain: An online 2-hr class offered monthly that teaches partners how to provide hands-on birth-support, comfort, and decrease labour pain.

If anyone’s looking for online prenatal classes please contact me.ย I teach all the sessions live but online so you can ask questions.

*****

Hospital Update

ONGOING SUMMARY of Current Practises in the Labour & Birth Unit and the Mother-Baby Unit:

  • The health region is not on the same timeline of relaxing restrictions as the SK gov’t. Restrictions are still in place at health care facilities.
  • All maternal patients and their designated family members/support persons will be screened for COVID-19 upon arrival at RGH and be required to have a temperature check, wear a mask, participate in hand hygiene and follow physical distancing guidelines.
  • Support persons/visitors who are symptomatic for COVID-19 or who have other risk factors will not be permitted.ย 
  • Masks are mandatory for partners and support persons throughout the hospital, except for when there’s no staff present in the Mother-Baby Unit. Labouring patients who pass screening are asked to wear masks as long as they’re comfortable doing so.ย 
  • All waiting rooms are closed. One primary support person is allowed with each maternal patient through registration and the assessment areas. The second support person should wait at home or somewhere outside the hospital until the labouring person is officially admitted and moved to a birth room.ย 
  • Support people coming in on their own, i.e. not with the labouring patient, can be screened 24/7 at the main RGH doors (14th St entrance). Do not use the ER doors unless you are a patient or are with one.
  • All maternal patients will be offered an optional COVID-19 swab once their admitted to the Birth Unit. Family members/support persons will not be offered a COVID-19 swab.
  • If the maternal patient tested positive for Covid at any time during their pregnancy, then their placenta will be sent for testing.ย 
  • There are 2 support persons (aged 18+) of the maternal patients choosing, allowed in the BIRTH ROOM; no swapping.ย 
  • The MOTHER-BABY UNIT allows new families to have 2 additional visitors at a time (11am-8pm). The “no-swapping rule” has been lifted in this unit. Visitors must be aged 18 and over, except siblings of the newborn who are permitted to visit with an adult.
  • Nitrous Oxide / “laughing-gas”/ Entonox is available, “๐‘ก๐‘œ ๐‘๐‘Ž๐‘ก๐‘–๐‘’๐‘›๐‘ก๐‘  ๐‘คโ„Ž๐‘œ ๐‘ ๐‘๐‘Ÿ๐‘’๐‘’๐‘› ๐‘ก๐‘œ ๐‘”๐‘Ÿ๐‘’๐‘’๐‘› (๐‘Ž๐‘ ๐‘ฆ๐‘š๐‘๐‘ก๐‘œ๐‘š๐‘Ž๐‘ก๐‘–๐‘ + ๐‘›๐‘’๐‘”๐‘Ž๐‘ก๐‘–๐‘ฃ๐‘’ ๐‘ƒ๐‘‚๐ถ ๐ถ๐‘‚๐‘‰๐ผ๐ท ๐‘ก๐‘’๐‘ ๐‘ก) ๐‘œ๐‘› ๐ฟ๐‘Ž๐‘๐‘œ๐‘ข๐‘Ÿ & ๐ต๐‘–๐‘Ÿ๐‘กโ„Ž ๐‘Ž๐‘ก ๐‘กโ„Ž๐‘’ ๐‘…๐‘’๐‘”๐‘–๐‘›๐‘Ž ๐บ๐‘’๐‘›๐‘’๐‘Ÿ๐‘Ž๐‘™ ๐ป๐‘œ๐‘ ๐‘๐‘–๐‘ก๐‘Ž๐‘™.”ย 
  • Waterbirth is no longer an option in the hospital, even for those under midwifery care. The installed bath-tub is available for comfort in labour.ย  Waterbirth is an option at homebirths when one is under midwifery care.
  • Breastfeeding is still being supported at RGH regardless of Covid-status. There are plans and protocols in place so that mother-baby can stay together if the birth-mom is at risk, has symptoms, or tests positive for C-19 in the immediate postpartum.ย 
  • All waiting rooms are closed. Food outlets have limited seating.
  • Galleys are closed to patients/visitors in both units. The nurses will get food for you in the birth unit but not in the mother-baby unit. Bring snacks! There is no access to the microwaves, kettles, food, water-ice machines. There is no access to the big fridges and freezers, but every room has a small mini-bar fridge.
  • The hospital does not provide warming tools other than blankets from the blanket warmer. If you like a hot-water bottle or heating pad, then bring your own. Staff are not allowed to take people’s heating devices to the microwave or kettle. You can use a plug-in device or fill a hot water bottle with hot tap water.
  • Bring what you would normally bring for your birth and hospital stay. Support people will be given a wristband so they can go to car later for extras and car-seat. You are still allowed to bring your pillow, clothing etc. – whatever you need for comfort.
  • Even though community restrictions are being lifted, great care should be taken with newborns once the family is home. Physical distancing and being only with members of the same household are still recommended. Anyone who enters the house can bring in pathogens/bugs.

03A47318

ย 

A TIMELINE OF PREVIOUS UPDATES

…. just in case you’re curious about what’s been coming and going and happening through the pandemic.ย  Note that several of these restrictions have been lifted. The list above is current.

June 08, 2022 – Good news! Nitrous Oxide / “laughing-gas”/ Entonox is available again in Regina, “๐‘ก๐‘œ ๐‘๐‘Ž๐‘ก๐‘–๐‘’๐‘›๐‘ก๐‘  ๐‘คโ„Ž๐‘œ ๐‘ ๐‘๐‘Ÿ๐‘’๐‘’๐‘› ๐‘ก๐‘œ ๐‘”๐‘Ÿ๐‘’๐‘’๐‘› (๐‘Ž๐‘ ๐‘ฆ๐‘š๐‘๐‘ก๐‘œ๐‘š๐‘Ž๐‘ก๐‘–๐‘ + ๐‘›๐‘’๐‘”๐‘Ž๐‘ก๐‘–๐‘ฃ๐‘’ ๐‘ƒ๐‘‚๐ถ ๐ถ๐‘‚๐‘‰๐ผ๐ท ๐‘ก๐‘’๐‘ ๐‘ก) ๐‘œ๐‘› ๐ฟ๐‘Ž๐‘๐‘œ๐‘ข๐‘Ÿ & ๐ต๐‘–๐‘Ÿ๐‘กโ„Ž ๐‘Ž๐‘ก ๐‘กโ„Ž๐‘’ ๐‘…๐‘’๐‘”๐‘–๐‘›๐‘Ž ๐บ๐‘’๐‘›๐‘’๐‘Ÿ๐‘Ž๐‘™ ๐ป๐‘œ๐‘ ๐‘๐‘–๐‘ก๐‘Ž๐‘™.” All maternal patients are screened on the way in (answer the usual questions re travel & symptoms) and then offered a swab-test once they’re admitted to the unit.

March 2022

  • Due to Covid, the Nitrous Oxide (“laughing gas”) is not available. It may be available again, depending on some supply issues.ย 
  • The Mother Baby Unit now allows new families to have 2 visitors at a time (11am-8pm) and they can be anyone you want. (The “no-swapping rule” has been lifted.)
    That said, postpartum hospital stays are usually short – only 1-2 days. There are many benefits to just resting with your new baby and saving the visitors for once you return home.
  • Note: The Labour & Birth Unit remains as is – 2 support persons per maternal patient, no swapping.

Feb 2022. The proof of vaccination / negative test requirements have been lifted.ย  Support persons no longer have to show proof of anything.ย 

Nov 8, 2021, partners, visitors, doulas, support persons, everyone EXCEPT the patient being admitted, must show proof of double Covid vaccine or a negative test within the past 72 hours from an SHA approved tester in order to enter SHA hospitals. Anyone who is not double vaxxed and wants to attend the birth might consider serial testing every 72 hours in order to be ready anytime.ย ย 

There are 2 support persons allowed in the BIRTH ROOM. From Saskatchewan Health Authority:

“Effective immediately, expectant mothers and families across Saskatchewan will now be permitted to have two designated family members/support persons present during their birthing experience. Designated family members/support persons are chosen by the mother and family and may include but are not limited to partners, family members, coaches, doulas or cultural support persons.

All maternal patients and their designated family members/support persons will be screened for COVID-19 upon arrival and be required to have a temperature check, wear a mask, participate in hand hygiene and follow physical distancing guidelines. Designated family members/support persons who are symptomatic for COVID-19 or who have other risk factors will not be permitted. The designated family members/support persons must be consistent during the duration of the patientโ€™s stay. They may leave the facility but cannot be switched out for another family member or support person. Only designated family members/support persons will be permitted at this time, other visitors, including siblings, will not be allowed.

All maternal patients will be offered an optional COVID-19 swab upon admission. Family members/support persons will not be offered a COVID-19 swab.

Summer 2020

โ—† Support people coming in on their own, i.e. not with the labouring patient, can be screened 24/7 at the main RGH doors (14th St entrance). They do not have to go to the ER doors.
โ—†A 24-hr support person who’s joining a birth or going to MBU for a maternal patient that has already been admitted can enter through the main 14th St doors at any time, 24/7. No need to go through the ER.
โ—† A support person entering the hospital with a maternal patient will be screenedwith the maternal patient.

Please note that while the 14th Ave entrance is open 24/7 with a security guard that can screen and let people in, the registration desk is only open from 6am-6pm. Support people can enter this door 24/7 because they are not patients (don’t need to go through the registration process).
ย 
If you’re in labour and going to RGH as a patient, then you’ll have to go to an entrance that has an open registration desk. On weekends, holidays and evenings/overnights, that will be the ER.

If you have to step outside and get back in, here’s how:

โ—† 14th St main entry has a security person around the clock. If you have your proof of screening and are wearing a band it’s easy to get back in 24/7. If you’ve not been screened yet, I recommend you start at this door. If they are unable to screen you, they will send you through the ER doors instead.
โ—† The ER can screen 24/7 but please save the ER capacity for people who need it.
โ—† 15th St admitting doors are locked overnight. The doors below MBU at 15th St parking lot are locked 24/7. You can not enter the 15th St side of RGH overnight. If you go out those doors, you’ll have to walk around to the 14th St entry.

If your 2nd support person is not at the birth but is invited to MBU, they will be screened on their way into the hospital. They must be named when you are admitted to LBU so remember to tell your nurse. You must get a coloured bracelet for them. I expect someone has to meet them outside the unit to give them the band that will grant them access to the MBU, but ask your MBU nurse about this.

โ—† “If the patient fails screening, she becomes a Person Under Investigation (PUI), therefore the support person now becomes a PUI as they have been in ‘close, prolonged contact with a PUI.’ The support will be sent home, however, the patient may have an alternative support person or people who pass screening. ” That means anyone who has been with the labouring person for more than 2 hours will not be allowed in if they are suspected of C-19/exposure.

Folks – you need to plan for this. Plan C. New support people who have not been with you for more than 2 hours AND who pass screening may be allowed into isolation. They will be gowned, masked, gloved throughout and will not be allowed to leave the isolation room. Food will be brought in.

โ—† Again, it’s up to you to ensure that a 2nd support person has been named so they can enter the unit. Ask your nurse about this.
โ—† Supports must be 19 years and older. (No, I’m not sure what happens in the case of teen pregnancy, young doulas and so on. This is just what I was told.)
โ—† The health region is not on the same timeline of relaxing restrictions as the SK gov’t. Restrictions are still in place at health care facilities.
โ—† You’ll see staff wearing masks throughout your stay.
โ—† Bring what you would normally bring for your birth and hospital stay. Support people will be given a wristband so they can go to car later for extras and car-seat. You are still allowed to bring your pillow, clothing etc – whatever you need for comfort.

Doctor

โ—† Labouring women are asked to wear the mask as long as they can stand to do so. Postpartum patients are asked to wear their masks when staff are in the room.

โ—† Masks are mandatory for partners and support persons throughout the hospital, except for when there’s no staff present in the Mother-Baby Unit.

โ—† People can wear whatever mask they want to enter the building. Public Health does have recommendations on personal masks (on the SHA site). However, once inside the building, people will go through screening and will be given medical masks to wear in the building (the blue ones with folds). The blue medical masks must be worn in all public spaces and the assessment area.

โ—† Nitrous-oxide (“laughing”) gas is available for pain management. If a tank is being used (instead of the tubes that go directly into the wall), then the maternal patient must have a negative Covid swab done prior to use.ย 
โ—† If you or baby are at high-risk for birth complications, you may be asked to use an epidural during labour to avoid the need for a general anaesthetic in case of an urgent/stat caesarean. Best to discuss this with your OB ahead of time so you can learn your options and make a plan.
โ—† Waterbirth is currently not an option in the hospital. Midwives are not lending pools out for home birth. If you have your own then waterbirth at home is still an option (contact me for info on where to get one).
โ—† The installed bath-tub is available for comfort in labour.
โ—† Breastfeeding is still being supported at RGH.
โ—† There are plans and protocols in place so that mother-baby can stay together if mom is at risk or has symptoms of C-19 in the immediate postpartum.
โ—† Even though some community restrictions are being lifted, great care should be taken with newborns once the family is home. Physical distancing and being only with members of the same household are still recommended. Anyone who enters the house can bring in pathogens/bugs.

โ—†I always tell people to bring their own hot water bottle or Magic Bag to the hospital. That’s because the hospital does not provide any warm tools other than blankets from the blanket warmer. They are lovely but they are not the same as a hot water bottle. The new update is that the staff are not allowed to take people heating devices to the microwave or kettle. Therefore if people want to use heat it will have to be a plug-in device or they can fill the hot water bottle with hot tap water in their own room. Stay warm and stay well during your visit!

โ—† Paid parking has resumed in the RGH parking lots. You will need cash for the main lot. Also, the 15th street parking is reserved only for people who have appointments or are being admitted to the hospital. Vehicles are being ticketed again on the streets around the hospital so no more free parking that way.

โ—† There is nowhere for the second support person to wait as all waiting rooms are closed. The second support person should wait at home or somewhere outside the hospital until the labouring person is officially admitted and moved to a birth room.

โ—† Partners/support persons will be provided with a mask at the entry doors. (Bring a big paperclip or string if you want to save sore ears.) Check out these tips for saving your ears from mask-pain.ย  Everyone must wear masks in the hallways. Labouring people do not have to wear a mask once they’re in their patient rooms in the birth unit and the mother-baby unit.

โ—† Food outlets now allow people to sit in.

โ—† Galleys are still closed to patients in both units. The nurses will get food for you in the birth unit but not in the mother-baby unit so people have to bring their own snacks. There is no access to the microwaves, kettles, food, water-ice machines. There is no access to the big fridges and freezers, but every room has a small mini-bar fridge.

Birth Room

๐๐ซ๐ž๐ง๐š๐ญ๐š๐ฅ ๐‚๐š๐ซ๐ž

โ— Attend appointments, diagnostics (ultrasound, lab) solo. Routine appointments might be done over the phone or spaced out. High-risk and special circumstances will still get the extra care they need.
โ— Midwifery offices are doing the discussion part of the consult by phone and then a quick in-person appointment for the hands-on part. They prefer pregnant patients attend alone but will allow partners. No other family members/friends/support are allowed.
โ— Anyone under midwifery or GP care who tests positive for C-19 at any point in their pregnant, birth or postpartum will be immediately transferred to OB care.
โ— If you’re an early-bird you may be asked to wait in your car until your appointment time.

๐€๐ง๐ญ๐ž๐ง๐š๐ญ๐š๐ฅ ๐‚๐š๐ซ๐ž (๐‹๐š๐›๐จ๐ฎ๐ซ & ๐๐ข๐ซ๐ญ๐ก)

โ— Early discharge is being offered as an option for those that are healthy and feel comfortable with newborn care. That means to go home a few hours after your birth instead of staying 24-36 hours.
โ— Anyone getting a cervidil induction will be monitored and then sent home to wait for labour to start, as per usual, then rescreened at RGH doors and LBU doors upon return.
โ— Support people are allowed at homebirths but must be screened. If anyone in the home (residents or support people) doesn’t pass screening, then the birth must be transferred to RGH. In that case, the one support person rule applies. Home birthers – screen your people before they come over!

๐๐จ๐ฌ๐ญ๐ฉ๐š๐ซ๐ญ๐ฎ๐ฆ ๐‚๐š๐ซ๐ž

โ— Doors that don’t have an admitting desk are locked tight; security will not let anyone in. That includes the convenient door just below the MBU.
โ— Families are being asked to stay in their room as much as possible.
โ— Support people may not visit any other patient areas.
โ— Food trays are being provided for new moms in the MBU.
โ— Breastfeeding class in the unit is still running but only birth mother and baby attend, and only up to 3 participants. If there are less than 3 maternal patients, then partners may be allowed to attend.
โ— Midwives and public health nurses are still providing postpartum home-visits. Some may be done by phone or video, depending on your needs.

Please contact me if you have any questions about this information or any of my services.